
Advanced minimally invasive procedures for structural heart conditions
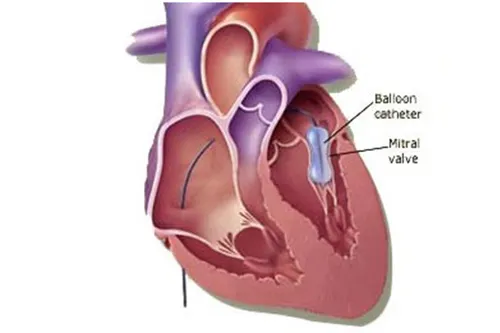
Mitral valvuloplasty, also known as mitral balloon valvotomy, is a minimally invasive procedure used primarily to treat significant mitral valve stenosis. Mitral stenosis occurs when the mitral valve becomes narrowed and does not open fully, making it harder for blood to flow from the left atrium into the left ventricle. This can increase pressure within the heart and lungs and may gradually affect the heart’s ability to pump efficiently. Mitral valvuloplasty helps improve blood flow by widening the narrowed valve opening without requiring traditional open-heart surgery.
During the procedure, a thin catheter with a specially designed balloon at its tip is guided through a blood vessel, usually from the groin, toward the heart. Once the balloon reaches the mitral valve, it is carefully inflated to separate the fused or stiffened valve leaflets and increase the valve opening. Mitral balloon valvotomy is most suitable for carefully selected patients whose valve anatomy is favorable and who do not have significant mitral regurgitation or other conditions that would make balloon treatment unsuitable.
Mitral stenosis can develop for several reasons, although rheumatic heart disease remains an important cause worldwide. Rheumatic fever can damage the mitral valve, leading to thickening, scarring and gradual fusion of the valve leaflets. Over time, this can restrict the normal opening of the valve and interfere with blood flow through the heart.
Less commonly, mitral valve narrowing may be related to age-associated calcification, congenital abnormalities or other structural conditions affecting the valve. The underlying cause, severity of narrowing and condition of the valve are important considerations when determining whether mitral valvuloplasty is an appropriate treatment.
Mild mitral stenosis may not cause noticeable symptoms for many years. As the valve becomes more severely narrowed, pressure can build up in the left atrium and the blood vessels of the lungs. Patients may gradually develop breathlessness, particularly during exercise, climbing stairs or other physical activity. Fatigue and reduced exercise tolerance are also common symptoms.
Some patients may experience palpitations due to abnormal heart rhythms such as atrial fibrillation. Other symptoms can include dizziness, swelling of the legs or feet and breathlessness while lying down. In advanced cases, symptoms may become more frequent and interfere with everyday activities. Early evaluation is important because significant mitral stenosis can progressively affect heart and lung function.
A detailed cardiovascular evaluation is essential for diagnosing mitral stenosis and determining its severity. The assessment generally includes a medical history, physical examination and echocardiography. Echocardiography provides important information about the structure and movement of the mitral valve, the degree of narrowing, blood flow across the valve and the effect of the condition on the heart chambers and pulmonary circulation.
Additional imaging may be recommended when more detailed information is required. Transesophageal echocardiography can provide a closer view of the mitral valve and may be particularly important before balloon valvuloplasty to assess valve anatomy and check for conditions such as blood clots in the left atrium. An electrocardiogram and other cardiac investigations may also be performed to evaluate heart rhythm and overall cardiovascular health.
Treatment for mitral stenosis depends on the severity of valve narrowing, symptoms, valve anatomy, heart function and the patient’s overall health. Patients with mild disease and minimal symptoms may be monitored regularly, while medications may be used to manage symptoms, control fluid retention or address associated heart rhythm problems. However, medications cannot physically widen a narrowed mitral valve.
For selected patients with significant rheumatic mitral stenosis and suitable valve anatomy, percutaneous mitral balloon valvuloplasty can be an effective minimally invasive treatment. During the procedure, a catheter-mounted balloon is positioned across the mitral valve and carefully inflated to improve the valve opening. Surgical mitral valve repair or replacement may be considered when balloon valvuloplasty is unsuitable, particularly when the valve is heavily calcified, significantly damaged or associated with substantial mitral regurgitation. The most appropriate treatment is determined after comprehensive imaging and assessment by an experienced heart valve team.
Following mitral valvuloplasty, patients are monitored to assess heart rhythm, blood pressure, valve function and the catheter access site. Echocardiography is commonly performed to evaluate the improvement in mitral valve opening and to check for any significant residual narrowing or mitral regurgitation. The duration of hospital observation varies depending on the patient’s condition and recovery.
After returning home, patients should follow their cardiologist’s recommendations regarding medication, physical activity and follow-up appointments. Medicines may be prescribed to manage heart rhythm problems, prevent complications or control symptoms when necessary. Regular echocardiographic monitoring remains important because mitral stenosis can recur or progress over time, particularly in patients with rheumatic valve diseases.
Mitral balloon valvuloplasty is a minimally invasive procedure, but as with any cardiac intervention, it carries potential risks. Possible complications include bleeding or bruising at the catheter access site, abnormal heart rhythms, blood-vessel complications and infection. The procedure can also occasionally result in increased mitral regurgitation if the valve becomes unable to close properly after balloon inflation.
Less common but more serious complications can include damage to the heart or surrounding structures, blood clots, stroke, cardiac perforation or the need for emergency surgery. The likelihood of complications depends on factors such as valve anatomy, severity of disease, age and overall health. Careful patient selection, detailed imaging and treatment by an experienced cardiac team help minimize these risks.
Persistent breathlessness, unexplained fatigue, reduced exercise tolerance, palpitations, dizziness or swelling of the legs should be evaluated by a cardiologist, particularly in individuals with a history of rheumatic fever or known heart valve disease. Symptoms that gradually worsen may indicate progression of mitral stenosis and should not be ignored.
Patients who have already been diagnosed with mitral stenosis should maintain regular cardiac follow-up even when symptoms are mild. A cardiologist can monitor valve function and determine when intervention may become appropriate. Severe or sudden breathlessness, chest discomfort, fainting, coughing up blood or rapidly worsening symptoms require urgent medical evaluation. Early diagnosis and appropriate treatment can help protect heart function and improve long-term outcomes.
Explore More: Aortic Valvuloplasty

Providing advanced, compassionate and evidence-based cardiac care with a focus on interventional cardiology, structural heart procedures and comprehensive heart health.
9:00 AM – 6:00 PM (By Appointment Only)
No WhatsApp Number Found!
WhatsApp us